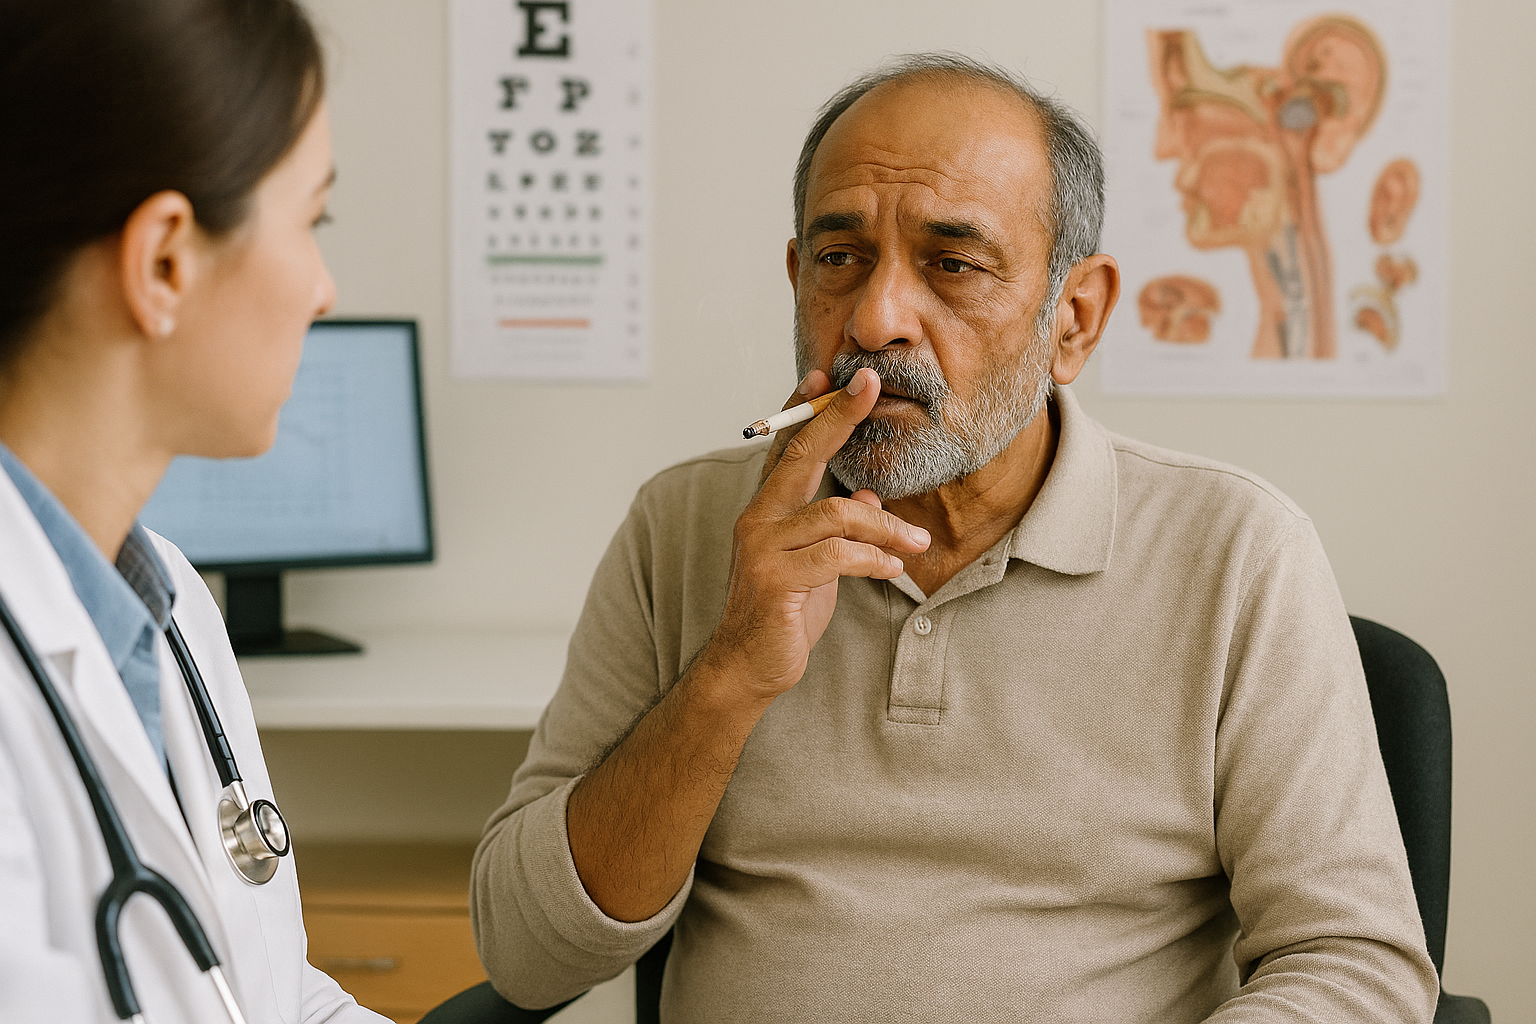
Mr. Khan, a 58-year-old man, attends his GP with a persistent cough and hoarseness. He’s noticed a change in his voice over the past few months and occasional difficulty swallowing. He smokes 20 cigarettes a day and has done so since his early twenties.
He’s polite, humorous, and insists he’s “not one to fuss.” He’s here because his wife insisted.
Examination reveals inflamed vocal cords and signs of chronic laryngitis. Referral to ENT confirms early-stage laryngeal changes consistent with tobacco-related damage. There is no malignancy, but the consultant warns that continued smoking will accelerate deterioration.
Mr. Khan listens quietly. Then he says:
“I’ve smoked all my life. It’s the only thing that calms me down.”
The ENT team explains the risks clearly. Mr. Khan nods, thanks them, and lights a cigarette outside the clinic.
At the follow-up, the GP gently revisits the topic. Mr. Khan shrugs:
“I know it’s bad. But I’ve lost too many things already. This is mine.”
He’s recently retired, lost two close friends, and feels isolated. Smoking is his ritual, his comfort, his identity.
The GP doesn’t push. Instead, she asks:
“What does smoking give you that you feel you’d lose without it?”
Mr. Khan pauses. Then he talks – about grief, loneliness, and the fear of change.
They agree to explore support options, not just for smoking cessation, but for rebuilding connection and routine. No ultimatums. Just partnership.